
Philosophy
4 min read
August 5, 2025
The 4 ages of medicine and the one we haven’t met yet

The 4 ages of medicine and the one we haven’t met yet

Healthcare is entering its most radical transformation yet. From reactive medicine to predictive intelligence, this article explores the four major eras of medical evolution — and why Medicine 4.0 will redefine how health is measured, managed, and optimised.

A defining moment in human health

We are standing at the edge of a defining moment in human history — one that will reshape how health is understood, managed, and lived. Most practitioners won’t see it coming until it’s already here. The pace of change is no longer linear; it’s accelerating at a parabolic rate.

Over the next ten years, healthcare will undergo a larger transformation than it has in the past two hundred. What once took generations to evolve will soon happen within a single career span.

Why the next leap will eclipse the last 200 years

In the 1850s, global life expectancy hovered around 35 to 40 years. In industrial cities such as Manchester, it was recorded as low as 26. Up to 40% of children died before the age of five. Since then, humanity has doubled its average lifespan — one of the greatest achievements in modern history.

But that magnitude of progress will soon appear slow compared to what lies ahead. To understand why, we must look at how medicine has actually evolved — not as a straight line, but as a series of paradigm shifts.

Medicine has never moved in a straight line

Medicine does not evolve gradually. It moves through distinct eras, each defined by its dominant questions, tools, and limitations. Every era solves the problems of its time — and creates the blind spots of the next.

Medicine 1.0: survival through intervention

The age of infection and emergency care (1800s–1950s)

The first modern era of medicine was built around one core mission: survival. Its philosophy was direct and uncompromising — find the problem, cut it out, kill the pathogen. The focus was acute illness, trauma, and infectious disease. Surgery, antibiotics, vaccines, early imaging, and public health measures transformed mortality rates almost overnight.

Breakthroughs such as germ theory, penicillin, antisepsis, and sanitation saved millions of lives. Yet this era had little understanding of long-term health. There was no framework for chronic disease, prevention, or personalisation. Medicine 1.0 was exceptional in emergencies, but largely blind to the slow decline of health over time.

Medicine 2.0: managing disease, not health

The rise of chronic disease frameworks (1950s–2010s)

As life expectancy increased, the medical challenge shifted. Infectious disease gave way to chronic illness. Medicine 2.0 emerged with a new goal: management. Cardiovascular disease, diabetes, cancer, and mental health disorders became the dominant focus.

Pharmaceuticals, specialist referrals, evidence-based medicine, and large clinical trials defined this era. Disease was framed as isolated dysfunction within individual organ systems. While imaging, surgical techniques, and electronic health records advanced rapidly, care became fragmented. Poly-pharmacy increased, symptoms were suppressed rather than resolved, and patients often cycled endlessly through the system.

Medicine 2.0 kept people alive — but rarely helped them thrive.

Medicine 3.0: personalisation, prevention, and patterns

From symptoms to systems (2010s–2025)

The limitations of chronic disease management gave rise to a new way of thinking. Medicine 3.0 reframed health as a dynamic, interconnected system shaped by genetics, environment, lifestyle, and time. The focus shifted toward root causes, prevention, and optimisation.

Functional blood work, genomics, microbiome testing, wearables, and systems biology expanded what was possible. Practitioners began looking for patterns rather than isolated markers. Precision nutrition and functional reference ranges replaced one-size-fits-all recommendations.

Yet this era introduced new challenges. Data became abundant but scattered. Interpretation demanded high cognitive load. Standards varied widely, access remained inconsistent, and outcomes depended heavily on practitioner experience. While powerful, Medicine 3.0 was difficult to scale.

Many believe this is the peak of modern healthcare.

Why medicine 3.0 is not the end point

Despite its advances, Medicine 3.0 still relies on humans to manually integrate overwhelming amounts of data, make predictions, and adjust protocols over time. It improved insight — but not intelligence. It offered tools — but not true systems.

The next era changes that entirely.

Medicine 4.0: intelligence, automation, and decentralised health

Predictive, adaptive, and continuously evolving care (2025–2040+)

Medicine 4.0 represents a fundamental shift in how health is defined and managed. Health becomes a continuously evolving dataset, updated in real time across all stages of life. The focus moves from reaction to prediction, from static plans to adaptive systems, from intervention to self-correction.

Artificial intelligence, machine learning, digital twins, predictive analytics platforms, continuous multi-biomarker wearables, synthetic biology, and autonomous medical systems will allow health trajectories to be forecast before disease manifests. Diagnostics will become ambient. Treatment will adapt dynamically. Biology itself becomes increasingly programmable.

But this transformation comes with real challenges — data privacy, equity, over-reliance on technology, loss of human connection, and the risk of eroding individual agency. Intelligence must be guided, not blindly trusted.

Building the infrastructure for medicine 4.0

This is where MyHealthPrac enters — not as a response to Medicine 4.0, but as an early foundation for it.

MyHealthPrac is a decentralised health management system designed to translate complexity into clarity. Built on over a decade of research, line-by-line journal reviews, and clinically informed logic, it transforms vast amounts of health data into actionable, root-cause solutions. Hard-coded algorithms, pattern recognition, and predictive frameworks allow practitioners to move beyond interpretation and into intelligence.

This is not theory. It is not a distant vision.

Not the future of health — the next standard

Medicine 4.0 is not coming someday. It is arriving now. And the systems built today will determine whether this new era empowers practitioners and individuals — or overwhelms them.

MyHealthPrac is being built to lead that transition.
Next news

Got plaque?

The conventional approach uses a process known as ‘Triple Therapy’ – this is the combination of two different antibiotics in-conjunction with a proton-pump inhibitor (which lowers HCL).

Not only does this have a low success rate, but it makes the host vulnerable to infection from other pathogens and parasites post-treatment. This is due to decreased stomach acid and a lessened ability to sterilise bacteria within food along with less competitive dominance within the gastrointestinal tract due to the eradication of the microbiota (pathogenic and beneficial species) within the gut, leaving available space to harbour unwanted bacteria.

H. Pylori is starting to develop resistance to antibiotics, making the conventional approach less and less effective – leading to the ‘thought’ process of adding more medication to the mix to overcome this resistance by using ‘Quadruple Therapy’.

The Health Protection Agency reports that the prevalence of H. Pylori antibiotic resistance varies within the UK depending on location, from 20-63% for metronidazole and 4.4-11% for clarithromycin. [11]

This is one factor explaining why as many as 20% of affected individuals have a reoccurring infection even after treatment.

Another factor for reinfection is the presence of H. Pylori in the oral cavity [1–3]; therefore, failure to eliminate H. Pylori from the mouth could lead to gastrointestinal reinfection.

Gingivitis and chronic periodontitis may be associated with H. Pylori infection and considered as a potential reservoir for bacteria. [4,5]

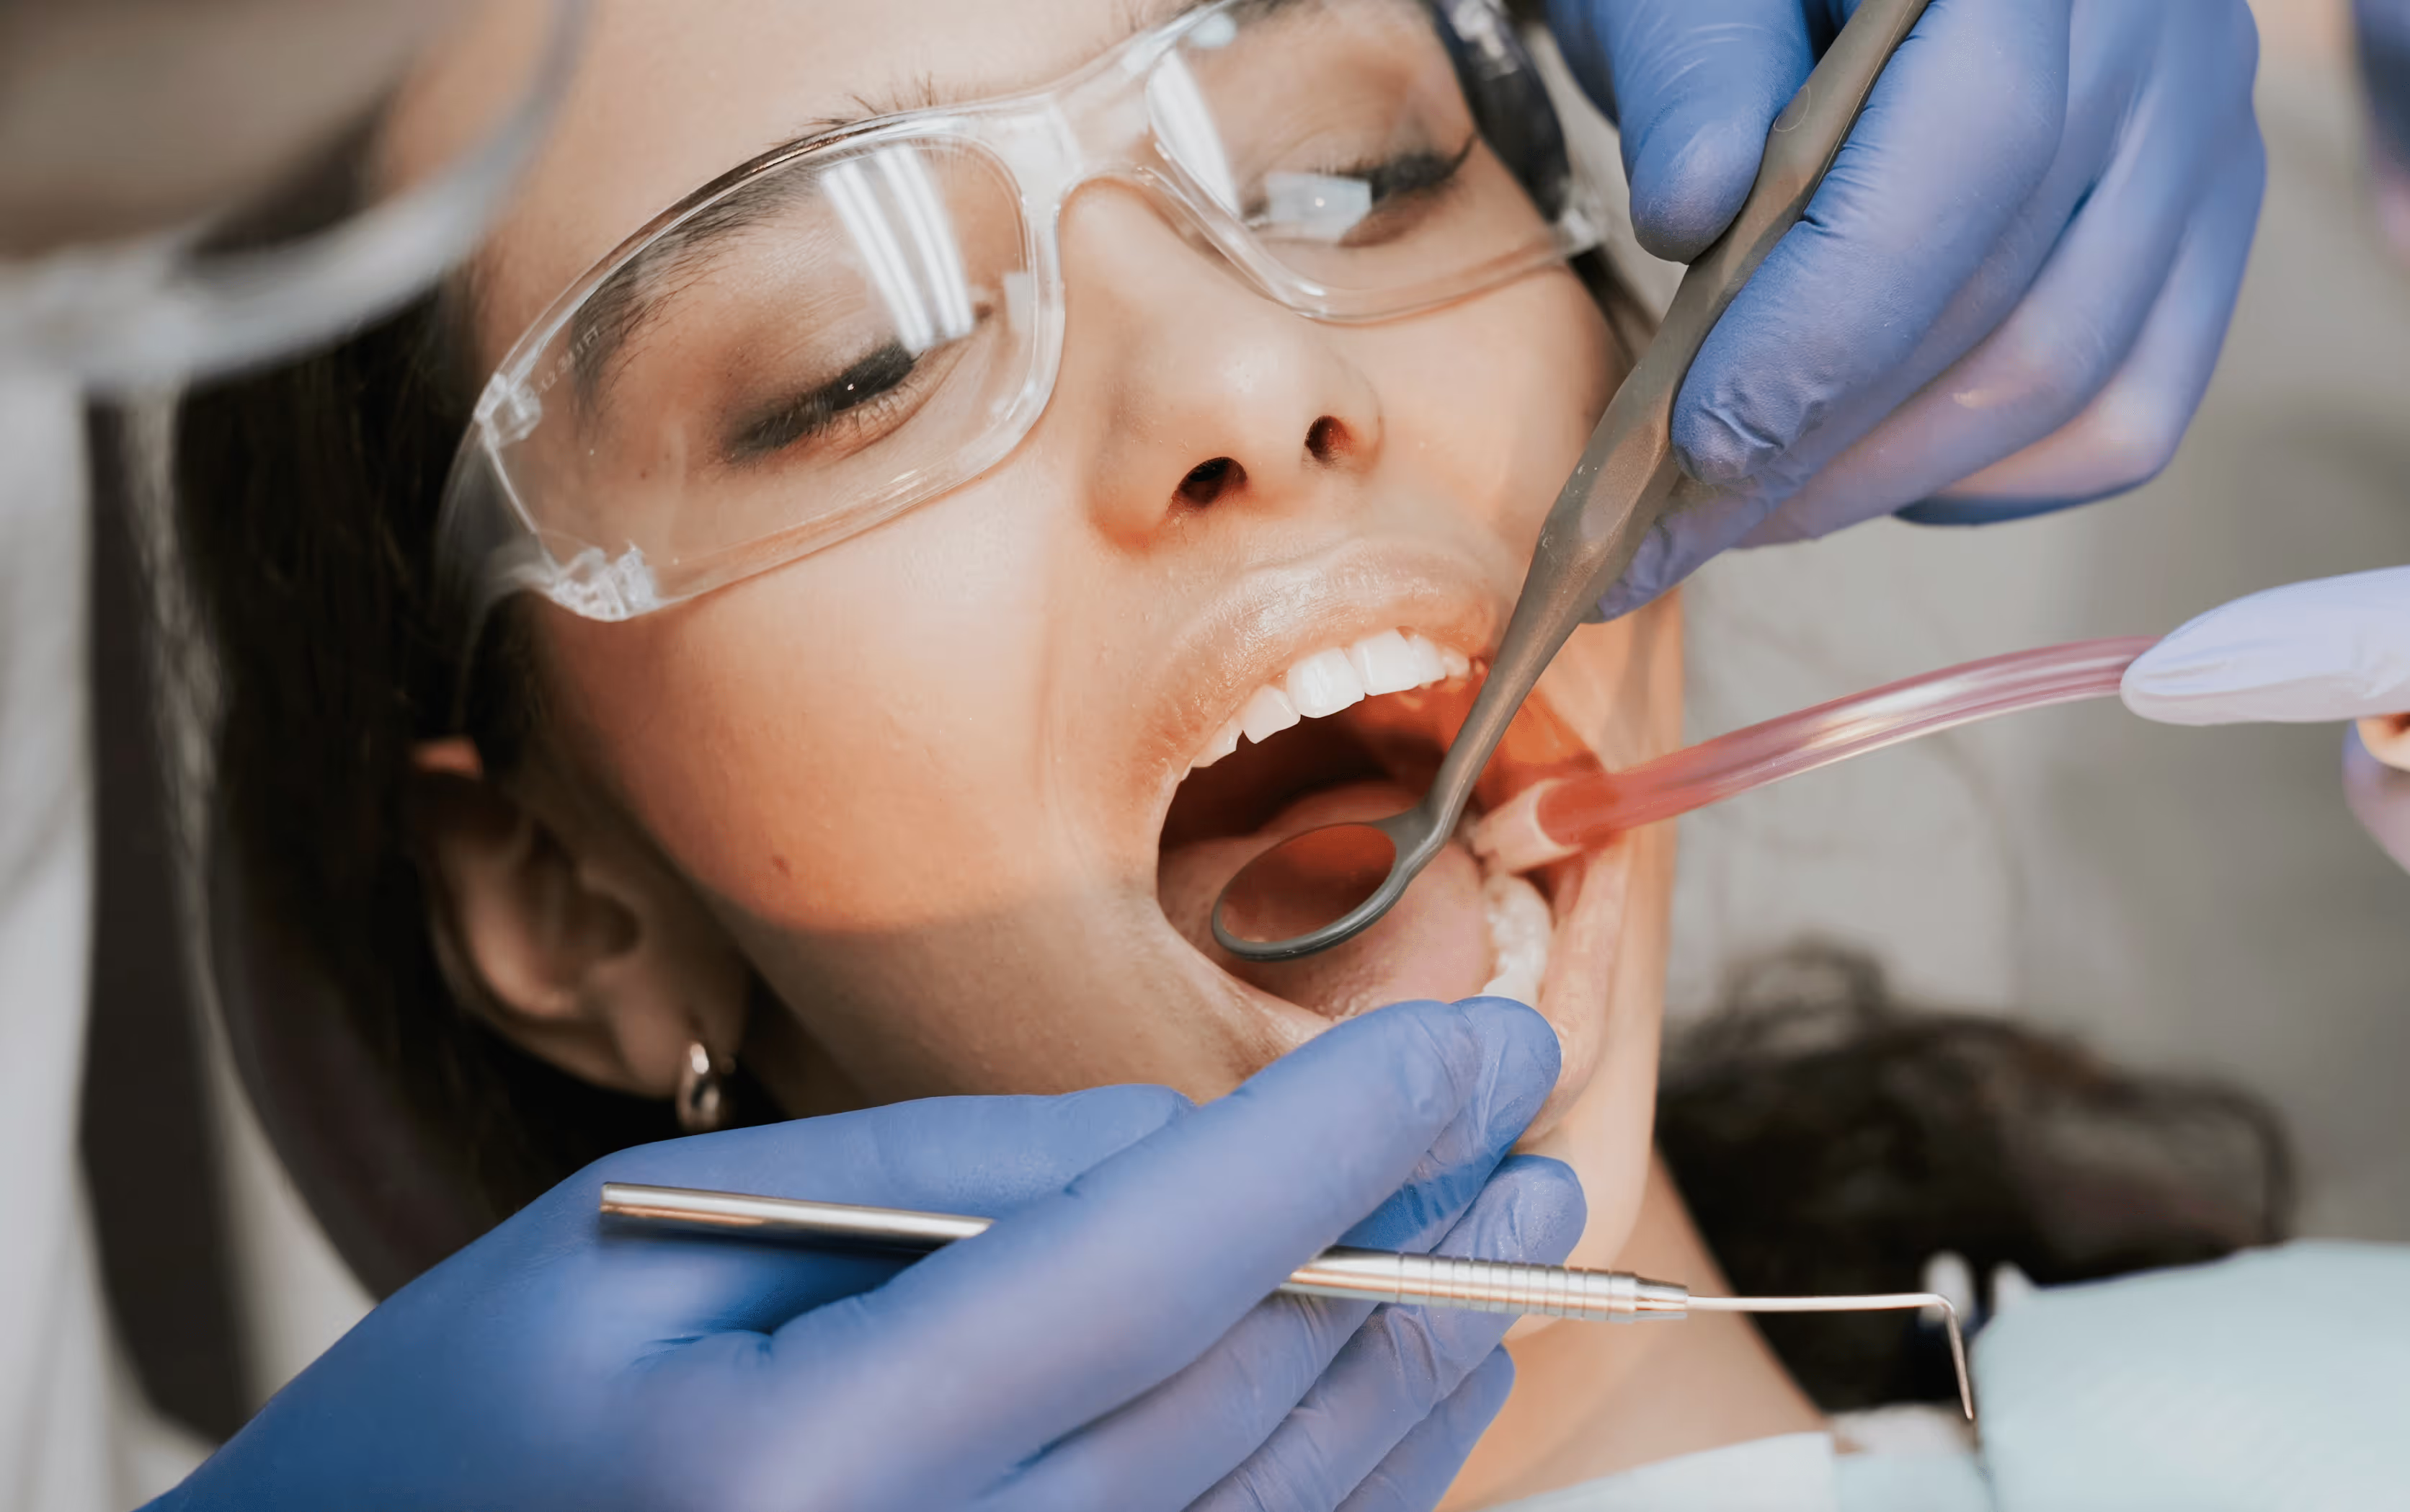
The plaque should be removed professionally, and oral hygiene procedures should be performed along with eradication strategies of H. Pylori [6] to increase the probability of success.

One could argue that an alternative approach yields much less risk to the host when compared with the iatrogenic complications and long-term hindrance from antibiotics (especially given that a single course of antibiotics can disturb the microbiome for unto 2-4 years post-treatment [12]).

The following has been found effective when addressing H. Pylori:

  • Bismuth subcitrate
  • Mastic gum
  • Goldenseal/Berberine
  • DGL Licorice wafers
  • Matula tea

The following foods have also been found beneficial:

  • Coconut oil
  • Manuka honey

All this has to be addressed with the appreciation of humans being a multi-dimensional and bi-directional organism.

Seeking advice from a trusted professional is always recommended when dealing with any health ailments.

References:

  1. Morales-Espinosa R, et al., Oral Microbiol Immunol. 2009
  2. Nguyen AM, et al., Oral Surg Oral Med Oral Pathol Oral Radiol Endod. 1995
  3. Miyabayashi H, et al., Helicobacter. 2000
  4. Gebara EC, et al., J Clin Periodontol. 2006
  5. Dye BA, et al., Am J Public Health. 2002
  6. Eskandari A, et al. Med Oral Patol Oral Cir Bucal.
  7. Abro AH, et al. J Ayub Med Coll Abbottabad. 2011
  8. Saudi J Gastroenterol. 2014
  9. J Gastrointestin Liver Dis. 2011
  10. J Gastroenterol Hepatol. 2011
  11. Surveillance of Helicobacter pylori antibiotic resistance in England and Wales; Public Health England, 2008
  12. Jernberg, C, et al. 2010
Gut Health
6 min read
Pylori, plaque and protocols
Reducing plaque, addressing oral health, and using targeted non-antibiotic strategies may improve eradication success while lowering long-term risks to the gut and immune system. A whole-body, professional-guided approach is essential.
December 10, 2022

How many of the following symptoms for iron deficiency do you have?

  • Non-Physical Symptoms
  • Anxiety
  • Cognitive dysfunction
  • Dizziness
  • Fatigue
  • Headaches
  • Lowered attention
  • Light-headedness
  • Mood swings
  • Post-partum depression

Physical:

  • Atrophy or enlargement of the taste buds
  • Compromised immune function
  • Hair loss
  • Koilonychia (Brittle, spoon-shaped nails)
  • Leg cramps / heavy legs
  • Lowered body temperature
  • Mouth sores
  • Pale skin complexion
  • Palpitations
  • Poor thyroid function
  • Skin problems
  • Shortness of breath
  • Swollen tongue
  • Restless legs
  • Pregnancy complications

Here are some of the mechanisms behind the above symptoms:

Iron is required for tryptophan hydroxylase activity, this enzyme converts tryptophan to 5HTP, the precursor for serotonin – the chemical brain messenger responsible for our happiness. Therefore with inadequate iron levels, serotonin production will be reduced.

Iron is also needed for tyrosine hydroxylase, this enzyme is essential for the production of dopamine – the chemical brain messenger that is responsible for our drive and motivation.

Iron is essential for the intracellular reception of T3. This reduces the activity of the main thyroid hormone thus lowering metabolism, energy, whilst leading to hair loss and other related factors.

Iron is required to make hemoglobulin. Hemoglobulin helps carry oxygen within the blood to tissues, an integral part of energy production. If iron is low, the body’s ability to produce energy is hindered therefore increasing the likelihood for fatigue. This same mechanism leads to reduced oxygen availability to the brain giving reason as to why headaches are also linked to iron deficiency.

The paling of the skin and inside of the eyelids is due to less hemoglobulin within the blood, as hemoglobulin gives blood its red pigmentation.

Reduced hemoglobulin levels result in less oxygen within the body. As a compensatory mechanism, the body will start to increase breathing and heart rate in hope to get more oxygen, thus leading to a shortness of breath and increased heart palpitations.

Conditions
6 min read
Symptoms of iron deficiency
When iron is low, serotonin, dopamine, thyroid activity, and oxygen delivery are all compromised, contributing to fatigue, mood changes, poor concentration, hair loss, shortness of breath, and cardiovascular strain. Identifying and correcting iron deficiency can be a key step in restoring energy, mental clarity, and overall physiological balance.
December 15, 2022

In a meta-analysis assessing the mineral intake of approximately 3,000 women. It found that eating an iron-rich diet (20mg per day) was linked to a 30-40% lower risk of developing premenstrual syndrome when compared to the lowest intake of iron (around 10mg per day) (Am J Epidemiol. 2013 May).

Menstruating women lose around 40% more iron per day when compared to men, with some studies stating how heavy menstrual bleeding is one of the leading causes of anemia in the developed world (Liu Z, et al. 2007).

The National Health and Nutrition Examination Survey indicates that 12-16% of non-pregnant women (aged 16-49 years) have iron deficiency, with 2-4% having anemia.

Increasing iron intake through diet and supplementation for two months has been shown to reduce PMS symptoms considerably in all anemic women (Mitesh Sinha et al. 2013).

Nutrition
6 min read
Iron and PMS
Iron and PMS
Menstrual blood loss increases iron requirements, making deficiency and anemia common contributors to PMS. Supporting iron intake through diet or targeted supplementation may significantly reduce symptoms, particularly in iron-deficient women.
December 9, 2022
Clarity, confidence, and real results start with one conversation. Let’s map your next chapter — together.

